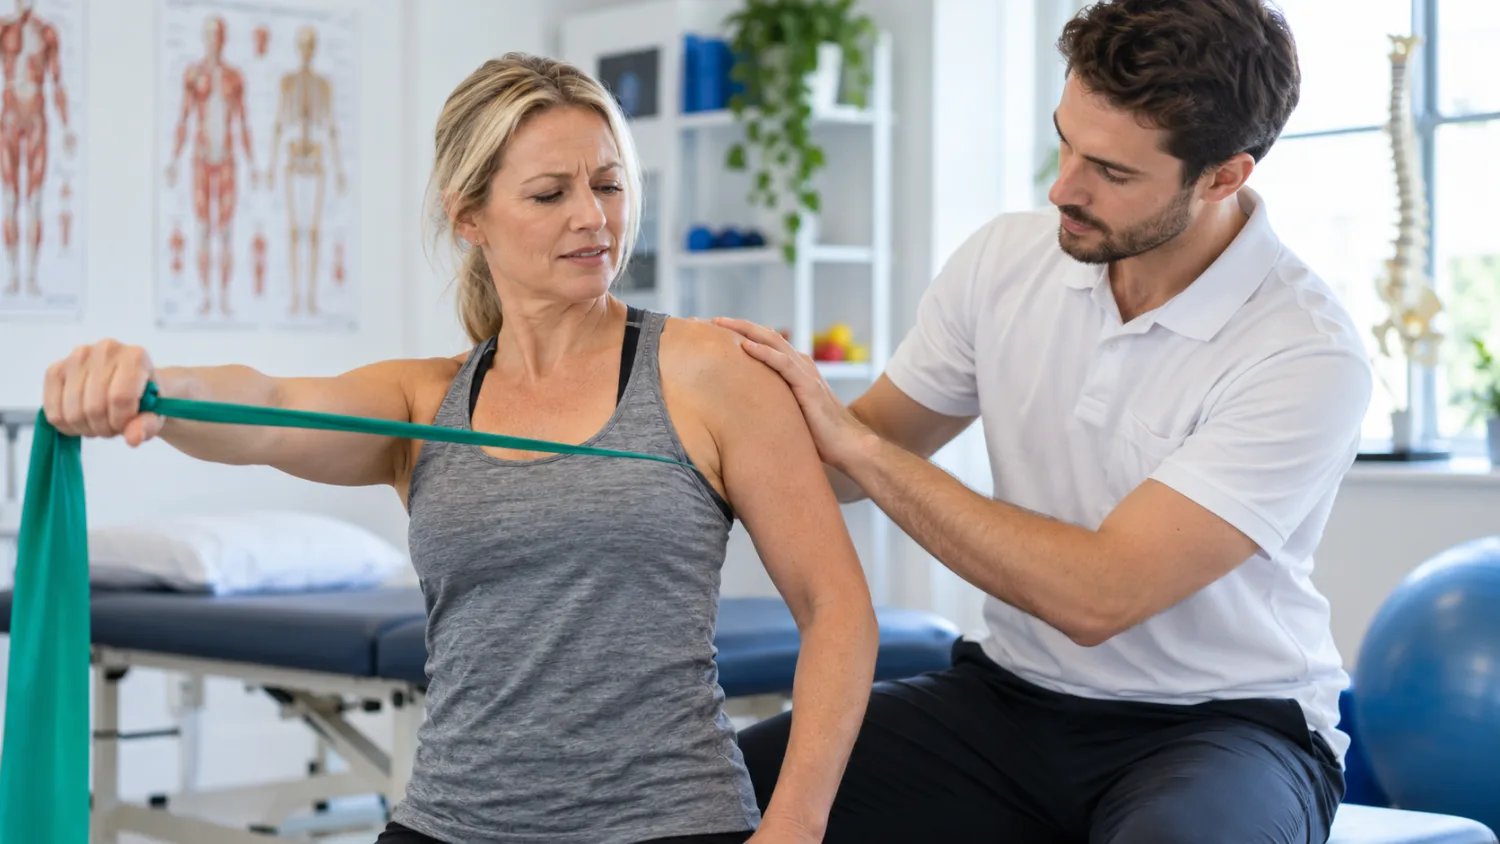
Rotator cuff pain is one of the most common causes of shoulder pain in adults.
It often causes an ache around the outside of the shoulder or upper arm, pain when lifting your arm overhead and discomfort when lying on the affected side at night.
The term rotator cuff refers to four muscles and their tendons that surround the shoulder joint. They help keep the ball of the upper arm centred in the socket and control lifting and rotation of the arm.
These tendons can become painful because of irritation, age-related changes, sudden increases in activity or injury.
You may hear several related terms, including:
- rotator cuff related shoulder pain;
- rotator cuff tendinopathy;
- subacromial pain;
- shoulder impingement;
- rotator cuff tear.
These terms do not all mean exactly the same thing, but symptoms can overlap considerably.
Most rotator cuff pain does not require an MRI scan straight away. In many cases, the diagnosis can be made from the history and physical examination, and symptoms improve with activity modification and a progressive exercise programme.
A scan becomes more useful when there has been significant trauma, marked weakness, persistent symptoms despite treatment or concern about a substantial tendon tear.
This guide explains what rotator cuff pain feels like, which exercises are commonly used and when ultrasound or MRI may actually change treatment.
What Does Rotator Cuff Pain Feel Like?
The pain is usually felt around the shoulder and the outer part of the upper arm.
It may travel towards the elbow, although pain extending into the hand or fingers is more suggestive of a nerve problem from the neck or elsewhere.
Common symptoms include:
- pain when lifting the arm;
- pain reaching overhead;
- pain putting on a coat or reaching into a cupboard;
- difficulty reaching behind your back;
- pain when lying on the affected shoulder;
- night pain that disturbs sleep;
- a painful or weak-feeling arm;
- clicking or catching in some people.
Some movements may be almost painless while others produce a sharp pain.
For example, typing at a desk may cause little difficulty, while reaching up to a shelf can be uncomfortable.
NHS musculoskeletal guidance notes that rotator cuff related pain is commonly worse when the arm is used above shoulder level and may also interfere with sleep.
What Causes Rotator Cuff Pain?
Rotator cuff pain does not always begin with an obvious injury.
It often develops gradually after the shoulder has been exposed to more load than it is currently used to handling.
Examples include:
- starting a new gym programme;
- painting or decorating;
- gardening;
- repeated overhead work;
- swimming or racquet sports;
- lifting heavier objects than usual.
Age-related tendon changes are also very common.
Small changes or even partial tears can be seen on scans in people who have no shoulder pain at all.
This is one reason scan results must be interpreted alongside your symptoms rather than treated as a diagnosis by themselves.
Rotator cuff pain can also begin after a fall, sudden pull or heavy lift.
That history matters because a traumatic injury is more likely to cause a significant tendon tear.
Rotator Cuff Pain vs Frozen Shoulder
Rotator cuff pain and frozen shoulder can both make lifting your arm difficult, but they usually behave differently.
With rotator cuff pain, movement may hurt, but the shoulder often still has a reasonable overall range.
With frozen shoulder, both active and passive movement become markedly restricted.
That means not only can you not lift or rotate the arm yourself — another person would also struggle to move the shoulder normally for you.
Frozen shoulder frequently causes:
- progressive stiffness;
- severe night pain early on;
- difficulty reaching behind the back;
- loss of external rotation.
If stiffness is the dominant feature rather than weakness or pain with specific movements, see our guide to frozen shoulder symptoms and treatment.
Shoulder arthritis can also cause pain and stiffness, particularly in older adults.
Can You Have a Rotator Cuff Tear Without Knowing?
Yes.
Rotator cuff tears become increasingly common with age, and some cause no symptoms at all.
A scan can therefore show a tendon tear that may or may not explain the pain.
Small degenerative tears are very different from a large traumatic tear.
A more concerning pattern is:
- a clear fall or sudden injury;
- immediate shoulder pain;
- sudden marked weakness;
- difficulty raising the arm afterwards.
In that situation, earlier clinical assessment and imaging may be appropriate.
NICE material on rotator cuff tears notes that ultrasound and MRI are both used when a tear needs to be confirmed.
What Exercises Can Help Rotator Cuff Pain?
Exercise is one of the main treatments for rotator cuff related shoulder pain.
The aim is not to force the shoulder through severe pain.
Instead, exercises gradually restore movement and increase the shoulder's ability to tolerate load.
NHS guidance recommends keeping the shoulder gently active rather than completely resting it and notes that shoulder exercises are often continued for at least six to eight weeks.
The exact programme is best tailored by a physiotherapist, but the following types of exercises are commonly used.
1. Pendulum movement
Lean forward slightly with one hand supported on a table or chair.
Allow the painful arm to hang loosely.
Gently move the arm:
- forwards and backwards;
- side to side;
- in small circles.
The movement should feel relaxed rather than forced.
This can help maintain movement when the shoulder is particularly sore.
2. Assisted shoulder flexion
Lie on your back or sit comfortably.
Use the unaffected arm, a stick or your hands together to help raise the painful arm upwards.
Move only as far as is reasonably comfortable.
This allows the shoulder to practise movement without forcing the painful muscles to do all the work.
3. External rotation with light resistance
Keep your elbow close to your side and bent to around 90 degrees.
Using a light resistance band, gently rotate your forearm outwards while keeping the elbow tucked in.
This targets the external rotator muscles of the cuff.
4. Isometric external rotation
If resistance-band exercise is too painful, start with an isometric version.
Stand next to a wall with your elbow by your side.
Press the back of your hand gently into the wall as though trying to rotate the arm outwards, but do not actually allow the arm to move.
Hold briefly, relax and repeat.
5. Supported shoulder raise
Raise the arm forward or slightly out to the side with a very light weight or no weight at all.
Start within a comfortable range and gradually increase movement and resistance as symptoms settle.
The goal is progressive loading rather than pushing through severe pain.
How Much Pain During Exercise Is Acceptable?
A completely pain-free programme is not always necessary.
Mild discomfort during rehabilitation can be acceptable, particularly when it settles quickly afterwards.
A useful practical rule is that exercises should not produce a major flare that lasts into the following day.
If your pain increases substantially after each session, reduce:
- the resistance;
- the range of movement;
- the number of repetitions;
- the frequency.
Then build up more gradually.
NHS guidance advises avoiding strenuous exercises or heavy gym equipment when you are first dealing with shoulder pain, while still keeping the shoulder moving.
A physiotherapist can help find a starting point that is challenging enough to strengthen the shoulder without repeatedly aggravating it.
If you are considering private treatment, our guide to private physiotherapy costs in the UK explains typical appointment fees.
Do You Need an Ultrasound or MRI Scan?
Not automatically.
For typical rotator cuff related shoulder pain without a major injury, NHS musculoskeletal guidance says imaging is often unnecessary initially.
A clinician can frequently make a working diagnosis from:
- the pattern of pain;
- range of movement;
- strength testing;
- specific shoulder movements;
- your injury and activity history.
The first treatment is often similar regardless of whether a scan shows mild tendinopathy, bursitis or a small partial tendon tear.
This usually involves:
- relative activity modification;
- pain relief where appropriate;
- progressive shoulder exercise;
- physiotherapy.
A scan becomes more valuable when the result could change management.
When ultrasound may be useful
Ultrasound can show:
- rotator cuff tears;
- tendon thickening;
- bursitis;
- calcific deposits;
- some dynamic movement problems.
It is relatively inexpensive, quick and does not involve radiation.
Its accuracy depends partly on the experience of the person performing the examination.
When MRI may be useful
MRI provides more detailed images of:
- rotator cuff tendons;
- muscles;
- cartilage;
- labrum;
- bone marrow;
- other structures around the joint.
An MRI may be particularly useful when:
- a large traumatic rotator cuff tear is suspected;
- there is marked weakness after an injury;
- symptoms remain unexplained;
- treatment has failed;
- surgery is being considered.
East Sussex NHS guidance specifically notes that MRI is more likely to be indicated for a suspected large traumatic cuff tear, while ultrasound can help in more persistent cases or where calcific deposits are suspected.
For private pricing, see our guide to private MRI, CT and ultrasound scan costs.
What Other Treatments Can Help?
Exercise and time remain central to treatment, but other options may be considered.
Pain relief
Paracetamol or anti-inflammatory medicines such as ibuprofen may help some people if they are medically suitable.
Topical anti-inflammatory gels may also be useful.
A pharmacist or clinician can advise if you have stomach, kidney, heart or medication-related reasons to avoid anti-inflammatory medicines.
Cold or heat
A wrapped ice pack can help after an aggravating activity.
Some people find warmth more comfortable for a persistent ache.
Corticosteroid injection
A steroid injection into the subacromial region can reduce pain temporarily in selected patients.
This may sometimes help someone participate in rehabilitation when pain is preventing exercise or sleep.
It is not generally viewed as a replacement for rehabilitation.
Repeated steroid injections may have disadvantages for tendon tissue, so they should not simply be repeated indefinitely.
Surgery
Most rotator cuff related pain does not require surgery.
Surgery is more likely to be considered for:
- significant traumatic tears;
- persistent weakness;
- large or full-thickness tears in selected patients;
- ongoing symptoms despite appropriate rehabilitation.
The decision depends on age, activity level, tear size, tendon quality and how much the symptoms affect daily life.
When Should You See a GP or Physiotherapist?
Arrange an assessment if:
- shoulder pain is not improving after around two weeks of sensible self-care;
- the pain is getting progressively worse;
- sleep is repeatedly disturbed;
- you are struggling to use the arm normally;
- weakness is becoming more noticeable;
- symptoms keep returning.
The NHS notes that many people can self-refer to local musculoskeletal or physiotherapy services without first seeing a GP.
Recovery can take time.
Some rotator cuff related shoulder problems improve within six to 12 weeks, while others take several months.
The shoulder generally responds better to gradual strengthening than to complete rest.
If symptoms started through sport or training, our guide to sports injuries, treatment and recovery covers rehabilitation principles more broadly.
When Is Shoulder Pain Urgent?
Seek urgent medical advice through an urgent GP appointment or NHS 111 if:
- you suddenly develop very severe shoulder pain;
- you cannot move your arm;
- the shoulder has changed shape;
- there is major swelling;
- pain followed a significant fall or accident;
- you have persistent numbness or pins and needles;
- the arm feels unusually hot or cold;
- you feel feverish or generally unwell.
These symptoms can indicate problems such as fracture, dislocation, significant tendon rupture, infection or nerve injury rather than uncomplicated rotator cuff irritation.
Sudden weakness after an injury is particularly important.
If you previously had reasonable shoulder function and then cannot raise the arm after a fall or heavy lift, arrange prompt assessment rather than trying weeks of exercises first.
Frequently Asked Questions
Where is rotator cuff pain usually felt?
It is commonly felt around the outer shoulder and upper arm. The pain may travel towards the elbow and often becomes worse when reaching overhead.
Does rotator cuff pain hurt at night?
Yes. Night pain is common, particularly when lying on the affected shoulder.
Can rotator cuff pain heal on its own?
Many cases improve with time, activity modification and exercise. Recovery often takes several weeks or months rather than a few days.
Should I rest a painful rotator cuff?
Avoid repeatedly aggravating activities, but complete immobilisation is usually not helpful. Gentle movement and gradual strengthening are generally encouraged.
Are exercises good for a rotator cuff tear?
Exercise is commonly used for many degenerative and partial tears. A large traumatic tear with sudden weakness needs assessment first because surgery may sometimes be considered.
How long should I do shoulder exercises?
NHS advice commonly recommends at least six to eight weeks of regular exercises, and many rehabilitation programmes continue for several months as strength improves.
Can I still go to the gym?
Usually, but temporarily reduce or modify exercises that sharply aggravate the shoulder. Avoid suddenly loading the shoulder heavily and rebuild strength progressively.
Do I need an MRI for rotator cuff pain?
Not in most straightforward cases. MRI becomes more useful when there has been trauma, marked weakness, persistent symptoms despite treatment or when surgery is being considered.
Is ultrasound enough to diagnose a rotator cuff tear?
Often, yes. A high-quality musculoskeletal ultrasound can identify many rotator cuff tears and other tendon problems. MRI provides additional detail when the diagnosis is uncertain or surgical planning is needed.
Can an X-ray show a rotator cuff tear?
No. Tendons are not well shown on ordinary X-rays. X-rays can instead help identify arthritis, fractures or some calcific deposits.
What is shoulder impingement?
The term is often used for pain arising from structures around the rotator cuff and subacromial space, especially when lifting the arm. Many clinicians now use the broader term rotator cuff related shoulder pain or subacromial pain.
How can I tell rotator cuff pain from frozen shoulder?
Rotator cuff pain usually hurts during particular movements but allows a reasonable overall range. Frozen shoulder causes much more global restriction of movement, including when someone else tries to move the arm for you.
Does a steroid injection fix the rotator cuff?
No. A corticosteroid injection may temporarily reduce pain and inflammation but does not repair a torn tendon or replace strengthening and rehabilitation.
When does a rotator cuff tear need surgery?
Surgery is most likely to be considered for substantial traumatic tears, persistent weakness or ongoing symptoms that have not improved with appropriate non-surgical treatment.
What is the biggest reason to get a scan early?
A major injury followed by sudden weakness or inability to raise the arm is one of the strongest reasons for earlier imaging because a significant traumatic tendon tear may be present.
This guide provides general information rather than an individual diagnosis or exercise prescription. Shoulder pain can arise from the rotator cuff, joint, neck, nerves and other structures. Seek professional assessment if symptoms are severe, traumatic, progressive or not improving.


