A private CT coronary calcium score in the UK typically costs around £150 to £350, although some providers charge more if the scan is bundled with a cardiology consultation, blood tests or a broader heart-health assessment.
The scan is quick, does not normally require contrast dye and gives you a number — the coronary artery calcium score, or Agatston score — that estimates how much calcified plaque is present in the arteries supplying your heart.
For the right person, that information can be useful.
For example, if your cholesterol is moderately raised and you are unsure whether starting a statin is worthwhile, a calcium score may sometimes help refine the discussion about your long-term cardiovascular risk.
But it is not equally useful for everyone.
A 30-year-old with very low cardiovascular risk may gain little from the scan. Someone who already has known coronary heart disease usually does not need a calcium score to prove that plaque exists. And if you currently have chest pain that might be angina, a simple calcium score may not be the most appropriate test.
This guide explains private CT calcium score costs in the UK, what the scan shows, who may benefit from paying for one and when the result is unlikely to change what you should do.
How Much Does a Private CT Calcium Score Cost in the UK?
A useful private self-pay range is approximately:
| Service | Typical private cost |
|---|---|
| CT coronary calcium score only | About £150–£350 |
| Calcium score with radiologist report | Often £200–£400 |
| Calcium score plus cardiology consultation | About £350–£700+ |
| Broader private heart-health package | Can exceed £500–£1,000 |
Prices vary by hospital, region and whether you need a referral before booking.
Some imaging providers advertise the scan as a standalone self-pay test. Others offer it only as part of a cardiology pathway.
Before booking, check whether the quoted fee includes:
- the CT scan itself;
- radiologist reporting;
- your written calcium score;
- any consultation before the scan;
- a follow-up discussion of the result.
If you are comparing private imaging more broadly, see our guide to private MRI, CT and ultrasound scan costs in the UK.
What Is a Coronary Calcium Score?
Coronary arteries supply blood to the heart muscle.
Over time, fatty material can build up inside their walls. This is known as atherosclerosis.
Some of that plaque eventually becomes calcified.
A CT calcium scan looks specifically for this calcification and measures how much is present.
The result is usually given as an Agatston score.
The British Heart Foundation explains that a higher calcium score generally means more calcified plaque and a higher risk of future heart attack.
The scan is different from a CT coronary angiogram.
A calcium score is simpler and usually does not use contrast dye.
A CT coronary angiogram uses contrast to produce more detailed images of the coronary arteries and can assess narrowing as well as plaque.
What Do the Numbers Mean?
Calcium scores are usually interpreted broadly like this:
| Calcium score | General interpretation |
|---|---|
| 0 | No detectable coronary calcium |
| 1–99 | Low level of calcified plaque |
| 100–299 | Moderate amount of calcified plaque |
| 300+ | High burden of calcified plaque |
These bands are useful shorthand, but age and clinical context matter.
A score of 100 in a 45-year-old may be more concerning than the same score in an 80-year-old because substantial calcium at a younger age suggests earlier development of atherosclerosis.
A score of zero is reassuring, but it does not mean your cardiovascular risk is literally zero.
Not all coronary plaque contains calcium, particularly in younger people.
Our separate guide to coronary artery calcium scores and what the numbers mean looks at result interpretation in more detail.
Who Might Benefit Most From Paying for a Calcium Score?
The scan is often most useful when you are in a grey area.
You may already know your blood pressure and cholesterol, have calculated cardiovascular risk, and still be uncertain whether preventive medication such as a statin makes sense.
A calcium score can sometimes provide an additional piece of information.
Potentially useful situations include:
- you are middle-aged with borderline or intermediate cardiovascular risk;
- you have a strong family history of premature heart disease;
- your cholesterol is raised but not dramatically so;
- you are reluctant to start a statin and want more information;
- your calculated risk may underestimate your true risk;
- you have several modest risk factors rather than one very severe one.
In those situations, detecting significant coronary calcium may make the case for intensive prevention much clearer.
On the other hand, a score of zero may support a more conservative discussion in some people, depending on the rest of the risk profile.
Who Probably Does Not Need a Calcium Score?
There are several situations where paying for the scan may add little.
You already have known cardiovascular disease
If you have already had a heart attack, coronary stent, bypass surgery or established coronary artery disease, you already know that atherosclerosis is present.
A calcium score is unlikely to change that.
Your cardiovascular risk is already clearly high
If you have very high LDL cholesterol, familial hypercholesterolaemia, significant diabetes-related risk or another strong indication for lipid-lowering treatment, a calcium score may not alter the treatment decision.
You are very young and low risk
Coronary calcium usually develops over time.
Young adults can have non-calcified plaque even when the calcium score is zero.
This makes the test less informative in very young people with otherwise low risk.
You have current chest pain
A calcium score is not generally the right self-booked test for somebody with new chest pain that could represent angina.
Chest pain requires clinical assessment because other investigations, including CT coronary angiography, may be more appropriate.
If you are currently experiencing worrying chest pain, see our guide to chest pain and when to seek urgent help.
How Does a Calcium Score Fit With QRISK?
In UK primary prevention, the main starting point is still conventional cardiovascular risk assessment.
NICE recommends using QRISK3 for adults aged 25 to 84 who do not already have cardiovascular disease.
QRISK uses information such as:
- age;
- sex;
- blood pressure;
- cholesterol;
- smoking;
- diabetes;
- kidney disease;
- family and medical history.
NICE currently recommends offering atorvastatin 20mg for primary prevention when the 10-year QRISK3 score is 10% or more, after appropriate discussion.
That means a calcium score is not a replacement for QRISK.
It is better thought of as an additional risk marker that may occasionally help when the decision remains uncertain.
For a wider explanation of these factors, see our complete guide to cardiovascular risk.
Can a Calcium Score Help Decide Whether to Take a Statin?
This is one of the main reasons people pay privately for the scan.
Imagine two people with the same moderately raised LDL cholesterol.
One has a calcium score of zero.
The other has a calcium score of 350.
Those results provide very different information about how much calcified coronary plaque has already developed.
A high calcium score can strengthen the argument for aggressively controlling modifiable risk factors, including LDL cholesterol, blood pressure and smoking.
A zero score may be reassuring, particularly in someone without major additional risk factors.
But a score of zero should not automatically be used as a reason to avoid statins.
For example, somebody with familial hypercholesterolaemia or another strong indication for treatment may still benefit from reducing lifelong LDL exposure even if no coronary calcium is yet detectable.
Our guide to statins, benefits and side effects explains how preventive treatment decisions are usually made.
What Does a Calcium Score Not Show?
This limitation is important.
The scan measures calcified plaque.
It does not directly show all types of coronary plaque.
Some plaque is soft or non-calcified.
Therefore:
A calcium score of zero does not prove that your coronary arteries are completely free of atherosclerosis.
This matters particularly in younger people, where plaque may not yet have accumulated enough calcium to be detected.
The scan also does not reliably tell you how much a particular artery is narrowed.
If doctors need detailed information about narrowing, a CT coronary angiogram or another investigation may be more appropriate.
What Happens During the Scan?
The test is relatively simple.
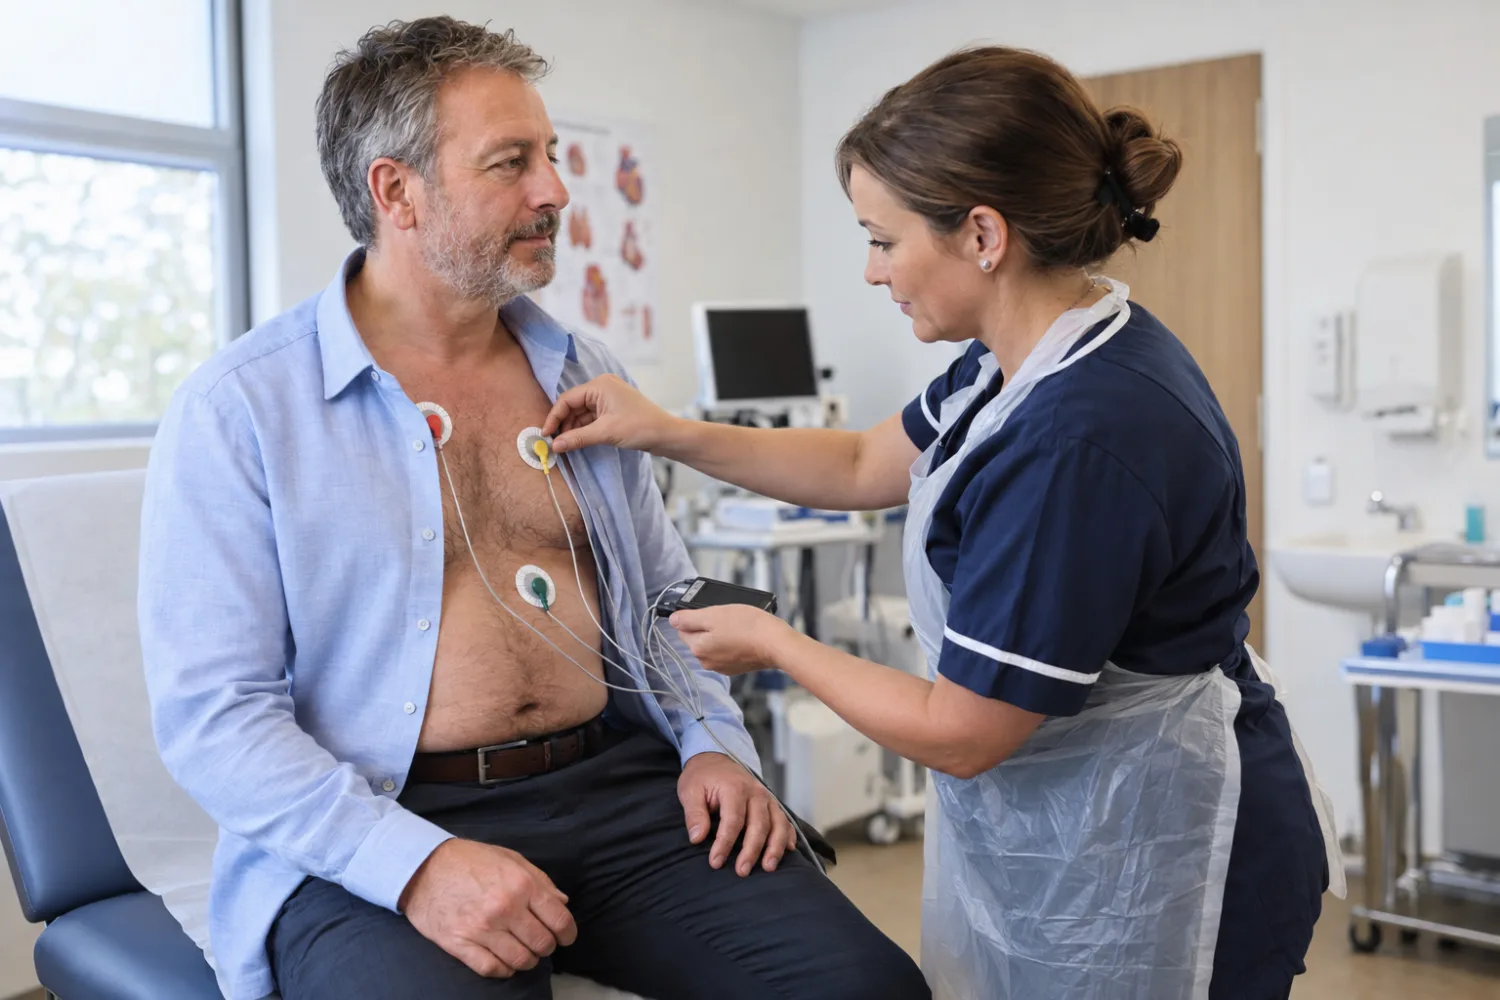
You lie on the CT scanner table while ECG stickers are placed on your chest so the scanner can synchronise images with your heartbeat.
The scan itself usually takes only a few minutes.
You do not normally need:
- an injection;
- contrast dye;
- sedation;
- a hospital stay.
The scanner takes rapid images of the heart and software calculates the amount of calcium present in the coronary arteries.
The radiologist then reports the score.
Some private providers send the report directly to you, while others require a referring clinician to discuss the result.
How Much Radiation Is Involved?
A calcium score uses X-rays, so there is some radiation exposure.
The dose is generally low.
The British Heart Foundation says the radiation exposure associated with heart CT scanning is low and comparable to background radiation accumulated over roughly a year, although the exact dose varies by scanner and protocol.
That does not make repeated scanning completely harmless.
Any medical radiation exposure should have a reasonable clinical justification.
This is another reason routine annual calcium scoring is generally unnecessary.
The test is also normally avoided during pregnancy unless there is a strong medical reason.
Should You Repeat the Scan?
Usually not frequently.
Coronary calcium changes slowly.
Repeating the test every year is unlikely to provide enough useful new information to justify repeated radiation and expense.
Some clinicians may consider repeating a zero score after several years if cardiovascular risk has changed substantially, but there is no universal schedule suitable for everyone.
More importantly, treatment should focus on reducing risk rather than trying to make the calcium score fall.
Statins, for example, reduce cardiovascular events but do not necessarily reduce the numerical calcium score.
In some circumstances plaque can actually become more calcified and stable while overall cardiovascular risk falls.
What Should You Do With a High Result?
A high score is not an emergency by itself.
It is evidence that coronary atherosclerosis is present.
The next step is to review your overall cardiovascular risk with a GP or cardiologist.
This may include:
- blood pressure;
- LDL and non-HDL cholesterol;
- ApoB;
- diabetes testing;
- smoking status;
- family history;
- exercise and diet;
- possible lipid-lowering medication.
If you have a calcium score but have not recently checked your cholesterol, our guide to cholesterol test results explains the standard measurements.
Additional tests such as ApoB or lipoprotein(a) may sometimes add further information, particularly where inherited cardiovascular risk is suspected.
A high score does not mean that an artery is about to close tomorrow.
It means preventive treatment deserves serious attention.
So, Is a Private Calcium Score Worth Paying For?
For some people, yes.
It is most likely to be worth the money when the result could realistically change what you do next.
A private scan may be useful if you are:
- in your 40s, 50s or 60s;
- free of known cardiovascular disease;
- at uncertain or intermediate cardiovascular risk;
- trying to decide how aggressively to treat cholesterol;
- concerned by a strong family history of early heart disease.
It is less likely to provide value if:
- you are very young and low risk;
- you already have established coronary disease;
- you already clearly need statin treatment;
- you are using it instead of investigating chest pain properly;
- you simply want reassurance despite having no meaningful risk factors.
The best question is therefore not:
“Can I afford a £200 scan?”
It is:
“Would knowing my calcium score change a treatment or prevention decision?”
If the answer is yes, the scan may be a sensible investment.
Frequently Asked Questions
How much is a private calcium score CT in the UK?
A typical standalone private coronary calcium scan costs around £150 to £350. Packages that include cardiology consultation or additional testing may cost £350 to £700 or more.
Can I book a calcium score without a GP referral?
Some private providers accept self-referrals, while others require referral from a GP or cardiologist. This depends on the imaging centre.
What is a good calcium score?
A score of zero means no detectable calcified coronary plaque and is generally reassuring. Any score above zero indicates some coronary calcification, with higher scores associated with greater cardiovascular risk.
Is a score of 100 high?
A score around 100 represents a moderate burden of calcified plaque in common classification systems. Its significance also depends on your age, sex and overall cardiovascular risk.
Is a calcium score of zero completely safe?
No. It is reassuring, but it does not exclude non-calcified plaque and does not guarantee that a future heart attack cannot occur.
Does the scan show blocked arteries?
Not directly. It measures calcified plaque burden rather than precisely showing the degree of narrowing in each artery. CT coronary angiography is more appropriate when detailed artery imaging is needed.
Does a calcium scan use contrast dye?
Usually not. A standard coronary calcium score is a non-contrast CT scan.
Is a calcium score the same as a CT coronary angiogram?
No. Calcium scoring measures calcified plaque. CT coronary angiography uses contrast dye to show the coronary arteries in greater detail and can identify narrowing.
How much radiation is there?
The dose is generally low, although it varies by scanner and protocol. Because it still involves ionising radiation, the test should be performed for a sensible clinical reason rather than repeated unnecessarily.
Can calcium in the arteries be reversed?
Coronary calcification itself is not usually reversed. Treatment focuses on slowing atherosclerosis and reducing heart-attack risk through cholesterol management, blood-pressure control, smoking cessation, exercise and other preventive measures.
Should I have a calcium score before starting statins?
Not routinely. UK statin decisions are generally based first on overall cardiovascular risk using QRISK3 and other clinical factors. A calcium score may sometimes help when the decision remains uncertain.
Should everyone over 50 have a calcium score?
No. Age alone is not enough reason. The scan is most useful when it adds information that could change management.
Does the NHS offer calcium scoring?
Calcium scoring can be used within NHS cardiac assessment pathways in selected circumstances, but it is not routinely offered as a general screening test to healthy adults simply because they request one.
Is a private calcium score worth £200?
It can be, particularly if you have borderline cardiovascular risk and the result would influence whether you start or intensify preventive treatment. If the result would not change anything, the money may be better spent on a GP or cardiology review and standard risk-factor assessment.
This article provides general information rather than individual cardiovascular advice. If you have chest pain, breathlessness on exertion or other symptoms suggesting heart disease, seek medical assessment rather than self-booking a calcium score as a substitute for diagnosis.